
DCSN 205 Project Case Assignment, Fall 2015
American University of Beirut · Operations Management · 10 pages









More DCSN 205 files
- Project Case Assignment – Individual · Fall 2015ProjectView
- Chapter Project Management · Spring 2012ProjectView
- Homework F · Fall 2015HomeworkView
- Homework Solution Chapter 9 · Fall 2015Chapter · with solutionView
- Homework Solution Chapter 8 · Fall 2015Chapter · with solutionView
- Homework Assignment 3 Sol · Fall 2015Homework · with solutionView
- Homework Assignment 2 Sol · Fall 2015Homework · with solutionView
- Final · Fall 2015Final examView
Show the text of this project
Introduction:
According to the document provided, the American University of Beirut
Medical Center (AUBMC) has been facing certain difficulties related to the
management of its staff in regards of how transport demands are dealt with.
From the beginning of the article, when the man entered Arwa Bou Ali’s
office, we can notice that some patients are just being kept aside waiting until their
turn to be transferred comes. This can be due to three main problems: is it because
the porters are slacking during job hours? Is it because of mismanagement of porter
staff? Or is it simply because that was a particularly busy day for the hospital?
Reading the rest of the article, we can see that the AUBMC is the only
hospital in the Middle East to have earned three different and international
accreditations, which make it one of the few institutions that should have a near
perfect patient management. Yet, as one can imagine, accreditations are only words
on a piece of paper, and small slip ups quickly become big problems that are often
hard to deal with. In our case, such slipups have led to many patients being stranded
and waiting to get the care they have requested and paid for.
In this report, we will identify possible shortcomings from the different
parties involved. We will be discussing the different methods for the AUBMC to
move forward with the issues at hand, as well as assessing the change they would
cause if implemented.
Should the AUB Medical Center engage in a full re-engineering
of its Patient Transport (PT) processes? If so, how should
AUBMC go about such a re-engineering? (Part 1)
AUBMC is recommended to do a process redesign due to the
current results it is experiencing, slow response time and dissatisfied
customers are a major concern which needs to be addressed. By
reengineering the process, it allows AUBMC to break down the existing
processes, scrutinize each sub-process and replace it with more efficient
processes. In addition, seeing that the load will be much higher in five
years it would be a good opportunity for AUBMC to lay a scalable and
efficient foundations to accommodate the much higher demand without
having to resort to another process reengineering after the launch of the
new building.
A process redesign involves a step-by-step approach to the process at
hand, thus we will present each step on its own.
Step 1: Reevaluating the purpose of the process
-
The process’ purpose is to transport patients across the medical
center with as little waiting time as possible. This increases
perceived patient-centered care, quality, service excellence and
operational efficiency, in line with the AUBMC goals set for the new
center.
-
After reviewing complaints, we noticed that the hospital staff was
complaining about transport jobs going unattended, this leads us
to another purpose, attend every transport request even if late.
While this might not increase the perceived service excellence, this
goal is aimed for the busy days.
-
Another complaint came from the dissatisfaction of the porters
regarding double booking which is decreasing the moral of the
workers, thus creating potential conflicts. The new process should
aim for keeping one booking reserved for one transporter only.
This will help boost staff moral and set a better working
atmosphere.
Step 2: Identifying Sub-optimal processes
Since the main process differs slightly between each department we will
classify sub-optimal processes by department.
-
General Issues
o
Floor clerk takes a clear message from the Registered
nurse
Adds an extra layer between the nurse and the
transporter leading to extra wait time. Limited to
handling one request at a time and is at the mercy of
being held up by his two other processes below,
blocking the request until another one is processed.
o
Floor clerk fills the log sheet
Paper based log sheet requires time to input, can take
more time due to complex names for example. Limits
ability to execute another process until this is done.
o
Floor clerk informs transporter about bed number, name
of patient and destination
Floor clerk is once again tied to this process and
cannot execute something else. The transporter
needs to visit the floor clerk to get this information,
costing the porter valuable time that should be
diverted to reducing patient transfer time.
-
Emergency Department:
o
Order filled by patient or companion
Does not give a good first impression of the patient
care and service excellence. What happens if patient
comes alone and cannot lose time in order to place a
transport order? If this is the first time a patient visits,
how would their companions know that they have to
personally place the order? This reliance on the
patient might give a sensation of irresponsibility and
this is not in line with the objectives set. In addition if
response time is not up to the expectations of the
patient he might order another transporter, thus
leading to double bookings.
-
OR & Outpatient Support Units:
o
Nurse hands over transport request to an orderly
While this is a direct line between the staff and the
transport (case of OR), it can cause bottleneck issues
described below.
o
An orderly was responsible for transporting, positioning,
lifting, cleaning the accessories and assisting the clinical
team when needed.
Too many tasks handled by an orderly especially when
in OR because he also has to assure transportation. In
case he is needed in assisting the clinical team and a
transport requests comes in he will be unable to
transport the patient thus increasing wait time on
patient side until the orderly is available. Too many
tasks are assigned to a single entity here.
-
Radiology:
o
Radiographer called the orderlies’ call center once the
radiology exam was completed and asked for patient to
be transported.
While this frees up resources by not tying any orderly
to one patient, it might lead to cases where a patient
finishes his radiology exam quicker or latter than
expected causing potential overlap of requests to the
orderly.
Step 3: IT and Technology Capabilities
One of the main issue we noted was the reliance on obsolete
methods of communication when it comes to contacting the
transporters. We cannot hope to improve efficiency and communication
time using paper log sheets and face-to-face information transmission
and mission tasking. We must be able to communicate information to the
transporters without having them come over and explain the task at
hand. This will require investing in a hospital-wide WAN network with
wireless capabilities which will allow transporters to contact and be
contacted on the go. This is will also require giving each transporter a
tablet where the application will reside. The Wi-Fi coverage is already
present and it can be leveraged in order to connect the transporters
together.
Step 4: Design the new process
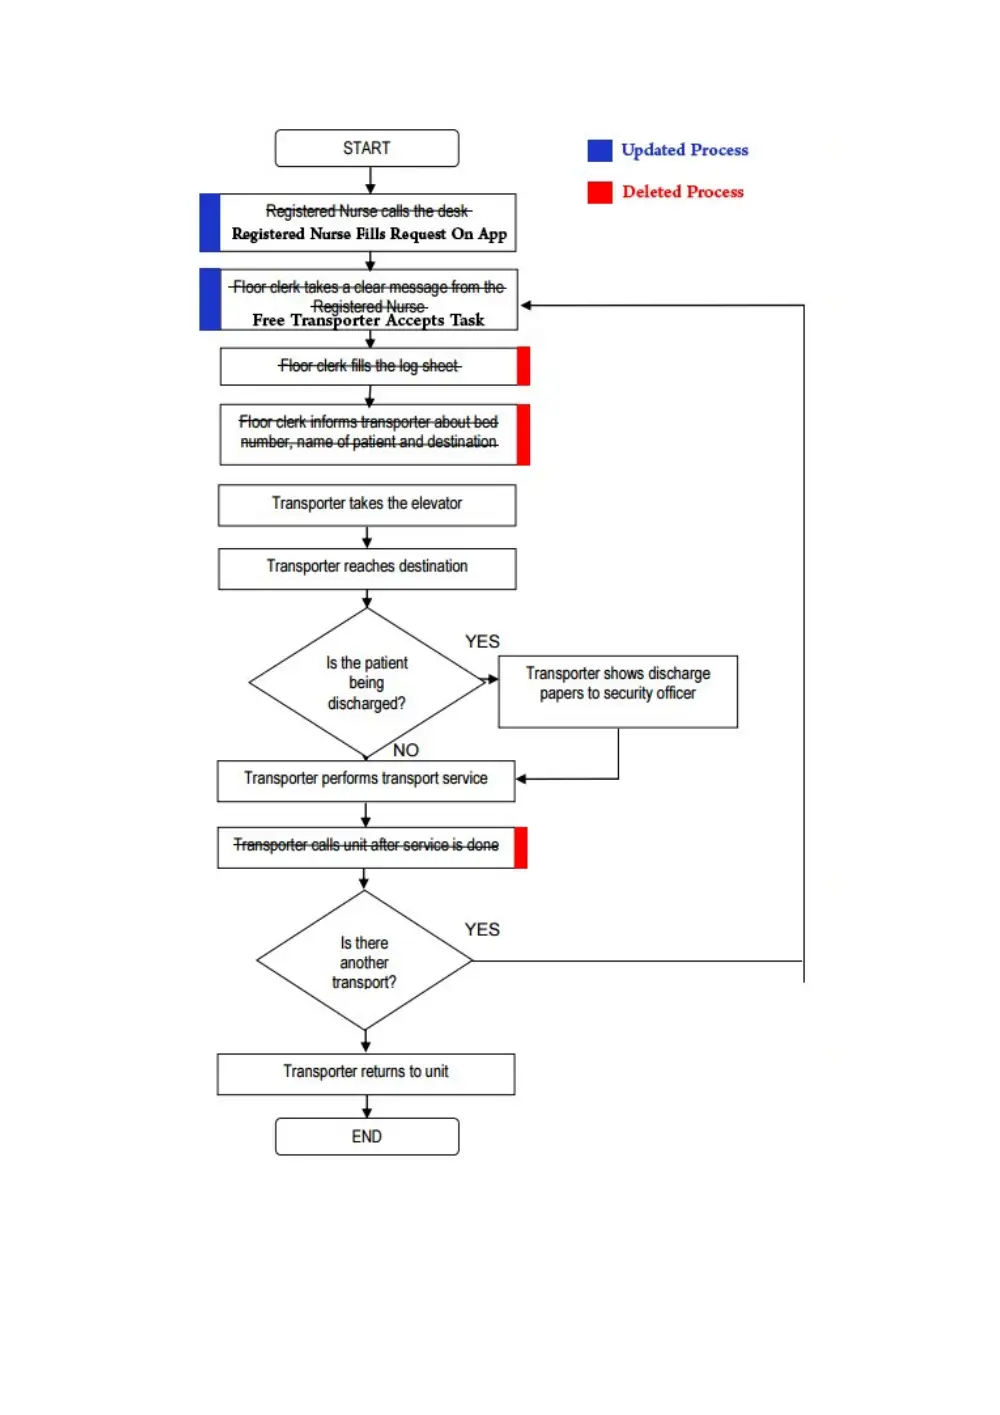
Based on Step 2 we can now propose a new process flow for each unit
that reflects the improvements that must be incorporated into the new
prototype.
-
General Issues
o
Old:
Floor clerk takes a clear message from the Registered
nurse
Floor clerk fills the log sheet
Floor clerk informs transporter about bed number,
name of patient and destination
o
New:
Registered nurse places a request for a free
transporter on her computer.
Free transporters which have marked themselves as
free after delivering a patient will get notified on their
tablet along with all the patient’s info.
First transporter to accept the job goes to the patient,
the job shows “In Process” then “Completed” when it is
done.
This way will allow us to bypass the Floor clerk and automate all
the processes directly. The system can also handle multiple
requests in parallel and has no theoretical bottleneck based on a
designed request/seconds throughput. Potential issues might be
related to Wireless connection issues which will require heavy
testing before being used on a daily basis.
-
Emergency Department:
o
Old:
Order filled by patient or companion
o
New:
Order filled by a clerk in addition to automated
machines.
Patient can install an application on his phone that
only works at the hospital if transportation is needed.
This approach gives patients a familiar element they can identify with
while at the same time providing optional self-service desks in order to
order a transporter. This is similar to airlines’ check-in booth nowadays,
most of them offer self-check in kiosks while keep the standard offices for
those who are unfamiliar with the newer technology.
Presented below is a General Control Chart summarizes the overall
changes
Key Performance Indicators: (PART 2)
If we are to take a look at the Key Performance Indicators, otherwise known
as KPIs, there are several international benchmarked indicators that any healthcare
institution should follow and abide by.
Relative to the case at hand, the AUBMC patient transport system can have
the following KPIs:
1- Time until the transport order is processed: This will be a measure that takes
into consideration the time between the moment a call is placed to the receptionist
and the time that a porter is actually assigned to a patient.
2- Time until arrival of porter to patient room: This will be a measure of time in
which we will see the amount of time lost between the assignment of a porter to a
patient and the time that the porter actually arrives to the room using the different
paths available in the facility.
3- Time until patient reaches his destination: This measure will be used to
assess the different routes that the porters use in order to transport the patients. Are
they using the most efficient route available for each order? or are they slacking and
using longer routes?
4- Time to pick up patient and take him back to his room: As we know, a
patient is never left lying around in the hospital, meaning that once the patient is
done with the x-ray or any test he was supposed to do, the doctor at hand cannot
leave him and just move on to another patient. This leads to the doctor at hand
having to keep the next patient waiting until the porter comes and takes the first
patient back to his room. Thus this will be a measure that shows whether time is lost
waiting for a porter to come for the trip back to the room.
5- Time spent outside the room: All in all, once the patient is hospitalized, he has
to spend the minimal amount of time outside of his room in order to minimize his
exposure to alien diseases, prevent and complications and thus reduce his overall
stay at the hospital. Thus, this will be a way to calculate the time that a patient
spends outside of his room from the moment that the porter first comes to pick him
up until he is sent back to his room.
6- Time spent on different porter orders: This will be a measure used to compare
how much time is spent on each type of porter order. It will help make the
transportation process more efficient by analyzing the different scenarios, and how
time is wasted in each department.
7- Time spent per patient at the hospital: The more time the patient spends at
the hospital, the more care he will need. Also, the longer the patient stays, the higher
the chances of him being contaminated by something other than his original
problem. Thus, it is more probable for a long-stay patient to require more than one
test or intervention, and thus more transport orders. If we manage to isolate long-
stay cases in a single ward, it would be useful to create a separate transport team
that will be dedicated for such patients, and also better trained to deal with them.
8- Number of beds outside of their rooms: This KPI will inform the
administration of the number of patients in transit at any given time during the day.
It is important to know such details in order to manage porters properly and be able
to direct them accordingly.
9- Urgent vs. Non-Urgent: This measure will indicate the urgency of a patient
transfer. For example, a patient needing a transport of the operating room is
considered more urgent than a patient going to take an X-ray. It is important to
mention that the first patient is only more important due to the fact that operation
slots are much more limited and time-oriented than an X-ray.
Potential solutions to the existing Patient Transport (PT)
problem: (part 4)
After identifying some of the problems in PT, which are mainly:
Miscommunication between staff members, doctors and the five teams of the
Patient Transport (PT) unit results in double booking. In addition to
miscommunication, there is an uneven workload and resource allocation among
and within the decentralized five teams of the PT unit that can be seen in exhibit
2 and exhibit 3 in the case study (i.e. the number of employees in each shift does
not always corresponds to the estimated workload distribution by shift). One
more problem is Using only one of the four existing elevators for porters which is
a constraint to complete the process of transporting the patients by waiting for
the one available elevator for the ten floors. More problems will arise when there
are an exceeded number of patients that need to be transported by the same
elevator. All these problems will result in lower productivity, more wastes1 and
longer process time. All of that will result in additional complaints. (Abdulhadi,
2015)
I suggest using some of the lean tools in process management developed from
the Toyota Production system (TPS), which mainly focus on increasing value and
eliminating waste.
Miscommunication results from lack of information, slow information
transactions or from misinterpreted information. One of the lean solutions is to
use visual control so no problems are hidden (Liker, 2004). For example, all team
members involved in PT can have a small electrical device managed by a central
unit that will inform them when they are needed to perform a specific task. In
addition, the electrical device can help identify the bed number and floor where
the transporter needs to transfer a patient. In this way the process is more visual
1 Ohno’s 7 Types of Waste: Defects in products , Overproduction of goods not
needed, Inventories of goods awaiting processing or consumption (work waiting on
workers), Unnecessary processing, Unnecessary movement of people,
Unnecessary transport of goods, Waiting by employees for process equipment
to finish work or for an upstream activity to complete. (Workers waiting on work)
(Liker, 2004)
and information can be transformed instantaneously. By eliminating the root
cause of miscommunication, we eliminated a non-value adding step to the
process hence eliminating one source of waste. This will increase the
productivity of the staff to handle patient transportation more efficiently and
more effectively.
There is an uneven workload and resource allocation between each team
member of the PT. Furthermore, the number of porters for each shift is not
evenly distributed for the estimated workload distribution represented in
exhibit 2 (Daouk-Öyry, Lina et al., 2015). In addition, as shown in exhibit 3,
the number of employees and the resources needed does not confirm with the
locations and the areas covered for each unit. This unevenness in the process
will result in overburden of the staff. This will result in decreasing staff
productivity, leading to a longer process time. A redistribution of both the
employees and the resources allocated for each team is required to ensure
that the workload is distributed evenly among the teams and the areas to be
covered. This application will eliminate unevenness and overburden which
according to the TPS are two kinds of wastes. The redistribution should be
based on proper forecasting to predict the number of patients on a monthly
basis to properly and evenly balance the employees and resources within
each team of PT unit. Another problem is the availability of only one elevator
of the existing four to be used for transporting patients. This resembles a
bottleneck in the process that will slower the whole process time. Situations
will get even more complicated when there is pressure on the usage of this
elevator. A solution for this problem would be to allocate another elevator to
be used by the PT unit whether it was using another existing elevator or
constructing a new elevator.